
Blog

A Sensory-Friendly Halloween: Costumes, Crowds, and Trick-or-Treating
Fort Myers occupational therapy teams know that Halloween can be one of the hardest nights of the year for a child with sensory differences. Itchy costumes, rubber masks, flashing decorations, doorbells, barking dogs, strangers in disguise, and a routine turned upside down all arrive at once, after dark. For many of our FOCUS families, the holiday brings a cautious optimism.
The good news is that some planning, most children can enjoy Halloween on their own terms. October is also Sensory Awareness Month, recognized each year by the STAR Institute for Sensory Processing, which makes this a good time to look at the holiday through a sensory lens. Halloween falls on a Saturday this year, which gives families more flexibility on timing.
The strategies below draw on occupational therapy, ABA therapy, and speech therapy. That reflects how FOCUS Therapy works with children every day, and how Halloween challenges a child: the body, the routine, and communication all at once.
Why Halloween Overwhelms
Halloween asks a lot of the sensory system. A costume presses on the skin in unfamiliar places. A mask covers the face, muffles hearing, and narrows vision. Decorations flash and cackle. Crowds move unpredictably. The night is dark, loud, and full of surprises, which are exactly what many children with sensory processing differences or autism find hardest to manage.
Halloween also breaks the rules children have learned. Children are taught not to take candy from strangers, not to walk up to unfamiliar houses, and not to go out after dark. On one night a year, all of that reverses. A child who relies on predictable routines has good reason to find that confusing.
Understanding the source of the stress is the first step toward planning around it.
Costumes: Start With Comfort
The costume is often the first battle, and it is usually a sensory one. Occupational therapists look at costumes the way they look at clothing in general: texture, seams, tags, tightness, and temperature.

The most successful costumes often start with clothing a child already wears comfortably. A favorite pair of soft pajamas, a hoodie, or a sweatsuit can become a cat, a dinosaur, or a superhero with a few additions. Store-bought costumes made of stiff polyester, scratchy netting, or elastic bands are frequent trouble spots. Removing tags, wearing a soft layer underneath, or cutting out the most irritating pieces can turn a rejected costume into a tolerable one.
Masks deserve special caution. Many children cannot tolerate something on their face, and masks also limit vision on a dark night. Face paint, a hat, or a simple headband with ears can create the look without the pressure. Southwest Florida adds another factor. Halloween evenings here are often still warm and humid, and heavy costumes can make a child overheated and irritable quickly.

Down Syndrome and Speech: How a Fort Myers Speech Therapist Builds Communication From Infancy
A Fort Myers speech therapist for Down syndrome often meets families long before a child says a first word, and that timing is deliberate. Communication starts in the first months of life, well before speech. It starts with eye contact, cooing, turn-taking, and the first gestures. For children with Down syndrome, the foundation for talking is built in infancy. The families who start early give their children the most time to build it.
October is Down Syndrome Awareness Month, recognized each year by the National Down Syndrome Society. It is a good moment to look at what the research says about speech and language in Down syndrome, why hearing deserves special attention, and why signs and communication devices help children talk rather than holding them back.
A Common Condition With a Distinct Communication Profile
Down syndrome is the most common chromosomal condition in the United States. According to CDC estimates, about 1 in every 640 babies is born with Down syndrome, roughly 5,700 births each year.
Every child with Down syndrome is an individual. Still, researchers have documented a communication profile that shows up across many children. Babbling often begins later. And a gap tends to open between what a child understands and what a child can say. A study published in Frontiers in Psychology described the most striking finding in the research this way: children with Down syndrome often have relatively strong receptive language, the ability to understand, alongside more significant delays in expressive language, the ability to produce words and sentences.
That gap matters. A child who understands far more than he or she can say may become frustrated. Adults may also underestimate the child. Researchers writing in Language, Speech, and Hearing Services in Schools noted that poor speech intelligibility can mask what a child with Down syndrome actually knows, which can lead to serious misconceptions about overall ability. Fort Myers speech therapy for a child with Down syndrome works to close that gap, so the child can show what he or she knows.
Why Speech Is Physically Harder

Pacifiers, Sippy Cups, and Speech: Why Fort Myers Speech Therapists Recommends Phasing Them Out Early
Most Fort Myers speech therapists are of the mind that once a child starts to talk, the pacifier and the sippy cup should be on their way out. A toddler needs a free mouth to babble, experiment with sounds, and try out new words. Heavy pacifier use is linked to smaller vocabularies, more ear infections, and dental changes that can make some sounds harder to produce. The sippy cup was designed as a short stop on the way to an open cup, not a permanent fixture. Neither one dooms a child’s speech. Both are worth retiring sooner rather than later.
Pacifiers Have a Place in Infancy
The case for phasing out pacifiers is about timing, not about whether pacifiers are good or bad. In the first months of life, they can serve real purposes. A 2025 review in American Family Physician found that pacifier use reduces the risk of sudden infant death syndrome, decreases discomfort during air travel, and helps control pain during shots and blood draws. The American Academy of Pediatrics recommends offering a pacifier when putting an infant to sleep, once breastfeeding is well established.
That window closes quickly. The AAP recommends weaning pacifier use during the second six months of life. The same review found that the health risks of pacifier use appear to increase after 12 months of age. Yet about half of children still use a pacifier at their first birthday, according to the review. For many families, the pacifier stays long after its benefits have run out.
What the Research Shows About Speech Sounds
The most careful study on pacifiers and speech sounds was published in 2021 in the International Journal of Language & Communication Disorders. Researchers Charlie Strutt, Ghada Khattab, and Joe Willoughby examined whether the duration and frequency of pacifier use affected how children’s speech developed.
Most speech outcomes in the study were not tied to pacifier use. The pattern that did emerge points straight at daytime habits. Frequent pacifier use during the day was associated with more atypical speech errors, the kind not usually seen in typical development. Nighttime use did not show the same effect. The authors noted that the evidence base is small and that the errors may resolve over time. Even so, the takeaway for parents is clear. A pacifier at bedtime is one thing. A pacifier in the mouth for hours of the day is a different matter.
Heavy Use and Smaller Vocabularies
A 2024 study took the question a step further. Researchers at the University of Oslo, Luis Muñoz, Natalia Kartushina, and Julien Mayor, published a study in Developmental Science examining pacifier use and vocabulary size.
They found that greater pacifier use over an infant’s life was associated with smaller vocabularies at 12 and 24 months. Later use mattered more than early use. Heavy pacifier use in the two months before a child’s second birthday was associated with a higher likelihood of scoring in the low range for vocabulary.
The study shows an association, not proof of cause, and the lead author said so directly. Fussier babies may use pacifiers more, and something about those babies could explain part of the difference. But the mechanism researchers propose is easy to understand. Babies learn to talk by babbling, playing with sounds, and imitating the people around them. A pacifier limits all three. Earlier experimental work found that infants holding a teething toy that restricted tongue movement temporarily had more difficulty telling certain speech sounds apart. A baby’s own mouth appears to help the brain process the sounds it hears.
A toddler with a pacifier in during most waking hours, at the age when vocabulary is exploding, is getting less practice than a toddler without one. That alone is a reason to cut back.
The Ear and Tooth Problems
The clearest risks of prolonged pacifier use affect speech indirectly, and they add to the case for weaning early.
The first is ear infections. The AAP’s recommendation to wean during the second six months of life is aimed at reducing the risk of otitis media, or middle ear infection. Repeated ear infections can leave fluid behind the eardrum and muffle hearing during the years when children are building their sound systems. FOCUS Therapy has written in more detail about how chronic ear infections can delay speech.
The second is teeth. Prolonged pacifier use is linked to dental malocclusion, including an open bite, where the front teeth do not meet. The American Academy of Pediatric Dentistry’s policy on pacifiers addresses these effects. An open bite changes where the tongue rests and moves, which can make sounds like /s/ and /z/ harder to produce cleanly. For more on how those sounds develop, see FOCUS’s sound-by-age timeline.
Sippy Cups: A Stepping Stone, Not a Fixture

The research on sippy cups is thinner than the research on pacifiers. Few studies test whether sippy cups affect speech directly. The concern rests mostly on how the mouth works.
A hard-spouted sippy cup with a spill-proof valve requires a sucking motion similar to a bottle. Drinking from an open cup or a straw requires more mature movements of the lips and tongue. The Minnesota Department of Health’s WIC guidance on cup transitions notes that sucking on a bottle or hard-spouted sippy cup frequently throughout the day can restrict the tongue’s range of movement. The guidance recommends open cups and straw cups without spill-proof valves.

What a BCBA Does: How a Fort Myers ABA Therapy Team Is Built
A Fort Myers ABA therapist is rarely working alone. Behind every session a child receives is a team with distinct roles, credentials, and responsibilities. Many parents meet the person who works with their child day to day without ever learning who designed the program, who reviews the data, or how often that person actually watches the sessions. Those questions matter more in Florida this fall than they have in years. Families who understand how Fort Myers ABA therapy teams are built can judge the quality of their child’s care for themselves.
Why Credentials Are in the Spotlight
Florida spends more on applied behavior analysis than any other state. According to reporting by the Florida Phoenix, Florida Medicaid spent $6.57 billion on ABA services between 2023 and 2025.
That spending prompted the Legislature to create an Applied Behavior Analysis Task Force within the Agency for Health Care Administration. The task force is examining clinical care models, quality metrics, service-authorization limits, potential caps on how long services last, and provider enrollment and billing standards. Its recommendations are due to the Governor and legislative leaders by December 31, 2026.
Whatever the task force recommends, one fact will not change: the highest quality of care and dedication brought by our Fort Myers ABA therapy team at FOCUS Therapy.

The BCBA: The Clinician in Charge
A Board Certified Behavior Analyst, or BCBA, is the clinician responsible for a child’s ABA program. The credential is issued by the Behavior Analyst Certification Board, an independent nonprofit that sets the standards for the profession.
Becoming a BCBA takes years. Candidates need a master’s degree or higher, graduate-level coursework in behavior analysis, and supervised fieldwork, which requires 2,000 hours under the standard pathway or 1,500 hours under a more intensive concentrated pathway. Then they must pass the BCBA certification exam. The BACB is tightening the eligibility pathways starting January 1, 2027. Under its 2027 BCBA requirements, applicants will qualify through either a degree from an accredited behavior-analysis program or a defined sequence of behavior-analytic coursework.
In practice, the BCBA does the work that shapes a child’s therapy. The BCBA conducts the initial assessment, identifies the skills a child needs to build and the behaviors that are getting in the way, and writes the treatment plan. The BCBA reviews session data to see whether the plan is working and changes it when it is not. The BCBA trains and supervises the registered behavior technicians who deliver much of the therapy, and leads parent training, which is often where progress at home begins.
Florida Medicaid builds its program around this role. Under the state’s Behavior Analysis Services Coverage Policy, services must be overseen by a Lead Analyst, and a BCBA credentialed by the BACB qualifies for that position.

Fort Myers OT Explains Why Bedtime Resistance May be a Sensory Problem
When bedtime falls apart every single night, a Fort Myers occupational therapist is not often the professional families think to call. Parents try earlier bedtimes, later bedtimes, sticker charts, and every routine a friend swears by. For some children, those things will help. But when a child’s nervous system is the thing standing between them and sleep, no schedule adjustment will resolve bedtime resistance.
Why Sleep and Sensory Processing Are Linked to Bedtime Resistance
Falling asleep requires a nervous system to move from alert to calm. For most children that shift happens quietly in the background. For children with sensory processing differences, it can be the hardest transition of the day.
Consider what bedtime actually asks. A child must stop moving after hours of accumulated input, tolerate the feel of pajamas and sheets, filter out household sound, accept darkness, and lie still without the movement their body may be actively requesting. Every one of those is a sensory demand, and they all arrive at once, at the end of a day when the child has the least regulation left to spend.
A Fort Myers occupational therapist may encourage that instead of asking why a child will not go to sleep, our occupational therapists at FOCUS Therapy ask what is happening in that room and in that body that makes sleep hard to reach.
What a Sensory Sleep Problem Looks Like
There are a few patterns worth noticing. A child who cannot settle without movement may rock, kick the wall, roll continuously, or ask to be squeezed. Their body is seeking proprioceptive input, the deep pressure information that comes from muscles and joints, because that input is organizing and calming.
A child who is overwhelmed rather than under-stimulated looks different. Pajama seams and tags become unbearable. The sheet feels wrong. The hum of the air conditioner, the ceiling fan, the light under the door, or the smell of dinner in the house all register at full volume. This child is not stalling. They are being asked to relax inside an environment their system is still actively processing.

Speech Sound Errors and Reading: Why a Kindergarten Concern Can Become a First-Grade One
Parents often ask their child’s Fort Myers speech therapist whether a preschooler’s speech errors will follow them into the classroom. The honest answer is the majority of children with speech sound differences learn to read without much difficulty. But a smaller group of kids may have a measurable risk into first grade — and researchers now understand fairly well which children those are. This knowledge can transform vague concerns into something a family can actually act on.
The Bridge Between Talking and Reading
Reading requires a child to break a spoken word into its individual sounds and match those sounds to letters. The skill that makes this possible is called phonological awareness, and it develops before formal reading instruction begins.
Phonological awareness follows a rough order. Children first notice rhyme and the beat of syllables, then isolate the first sound in a word, then blend sounds into a word, and finally segment a whole word into its parts. A kindergartner who can tell you that “cat” starts with /k/ and ends with /t/ is doing the work that decoding will require in a few months.
Note that children does not analyze words using the sounds in the air. They analyze words using the sound representations stored in their own mind. If those stored representations are fuzzy or organized in an unusual way, the analysis gets harder, no matter how bright the child is or how much they love books.
Not All Speech Errors Carry the Same Weight
Clinicians distinguish between articulation errors and phonological errors. An articulation error involves difficulty producing a particular sound, like a lisped /s/ or a /w/ substituted for /r/. The child’s underlying sound system is intact. The mouth simply has not caught up.
A phonological error is rule based and affects whole categories of sounds. A child who drops every final consonant, so that “cat,” “cap,” and “can” all come out as “ca,” is not struggling with individual muscles. They are operating on a pattern that simplifies the sound system itself.
Research published in the Journal of Speech, Language, and Hearing Research followed 123 children and analyzed their speech errors at ages five and six against their literacy at ages seven to nine. Phonological errors, but not articulation errors, predicted phonological awareness, letter knowledge, and later literacy, even after accounting for the children’s language skills. Sequencing difficulty, meaning trouble organizing sounds in order, showed the strongest relationship of all.
For a family whose kindergartner has a charming lisp and nothing else, that finding is genuine reassurance. For a family whose child simplifies whole patterns of sounds, it is a reason to look closely at preliteracy skills now rather than waiting.
The Second Risk Factor Is Language, Not Speech

When Insurance Cuts Your Child’s Authorized Hours
When a letter arrives indicating your health insurance provider is cutting your child’s authorized therapy hours, it often lacks a clear explanation. Families receiving Fort Myers ABA therapy, speech therapy, and occupational therapy at FOCUS Therapy have more than once expressed frustration with the dense language in these letters, as well as the seemingly arbitrary cuts and no clear sense of what to do next.
When the number of hours your insurer is authorizing does not match the evidence-based recommendations of your child’s experienced, multidisciplinary therapy team, we will work families to help advocate for coverage of the services your child needs to reach their goals.
Note that the following is not a substitute for one-on-one advice and it may not cover your exact situation. Rather, it is a general map of the process so you know what questions to ask, what deadlines to watch, and who to call first.
What a Reduction in Therapy Hours Actually Means
Insurance authorization is the process by which a plan agrees in advance to pay for a set amount of service over a set period. When a plan reduces hours, it is saying the paperwork in front of its reviewer did not establish medical necessity for the amount requested.
That is a narrow finding, made usually in minutes by someone who has never watched your child work, often based on a few key words in a file. Reviewers see numbers and narrative summaries. They do not see the session where your daughter requested something with words for the first time, or the month your son stopped bolting in the parking lot.
Progress can even work against a request, because plans sometimes read improvement as evidence that less support is needed. But at FOCUS Therapy, our therapists understand that emerging are also the skills most likely to be lost without continued practice.

The Age of Toys Is Not Over: What Toy Story 5 Gets Right About Screens and Child Development
Pixar spent four films asking what happens to a toy when a child outgrows it. Toy Story 5 asks a harder question: What happens to a child when nothing gets outgrown, because nothing gets played with?
Bonnie is 8 now. She still plays with Jessie and Bullseye, but she cannot seem to make friends with the other kids in the neighborhood, because no one plays with toys anymore.
A discarded toy delivers the film’s thesis in five words: “The age of toys is over!”
Jessie climbs onto a roof and sees screens glowing in every house on the block. Bonnie’s parents buy her the frog-shaped tablet, Lilypad, with the hope that it help her socialize more with kids her own age.
Our Fort Myers ABA therapists recognize that the movie’s point is not that screens are all bad. It is that “toys are for play, but tech is for everything.” What Bonnie needed was another kid in the room. No device could be one. Screens do not harm children by doing something to them. The harm is in the hours of social-emotional development they are losing as a result. The impacts can be even more outsized for children with diagnoses like autism and ADHD who area already struggling with important life skills like interpersonal communication and impulse control.
What Kids Lose With Too Much Screen Time
The American Academy of Pediatrics focused not on the mechanism but the displacement in its February 2026 policy statement, Digital Ecosystems, Children, and Adolescents. High quality media built around children’s developmental needs can support learning and well-being. But media built to maximize engagement and commercialization encourages prolonged use — and that prolonged use displaces sleep, movement, and social development. The AAP states plainly that media and children “cannot be viewed solely through the lens of individual child behaviors or screen limits alone.”
The AAP’s current framework replaces the old clock-based rule with five questions, the 5 C’s: Child, Content, Calm, Crowding out, and Communication. Crowding out is the one that matters most here. What is the device getting in the way of?
For most children, the answer is sleep, movement, and other people – in that order.
Hearing Loss, Chronic Ear Infections, and Delayed Speech
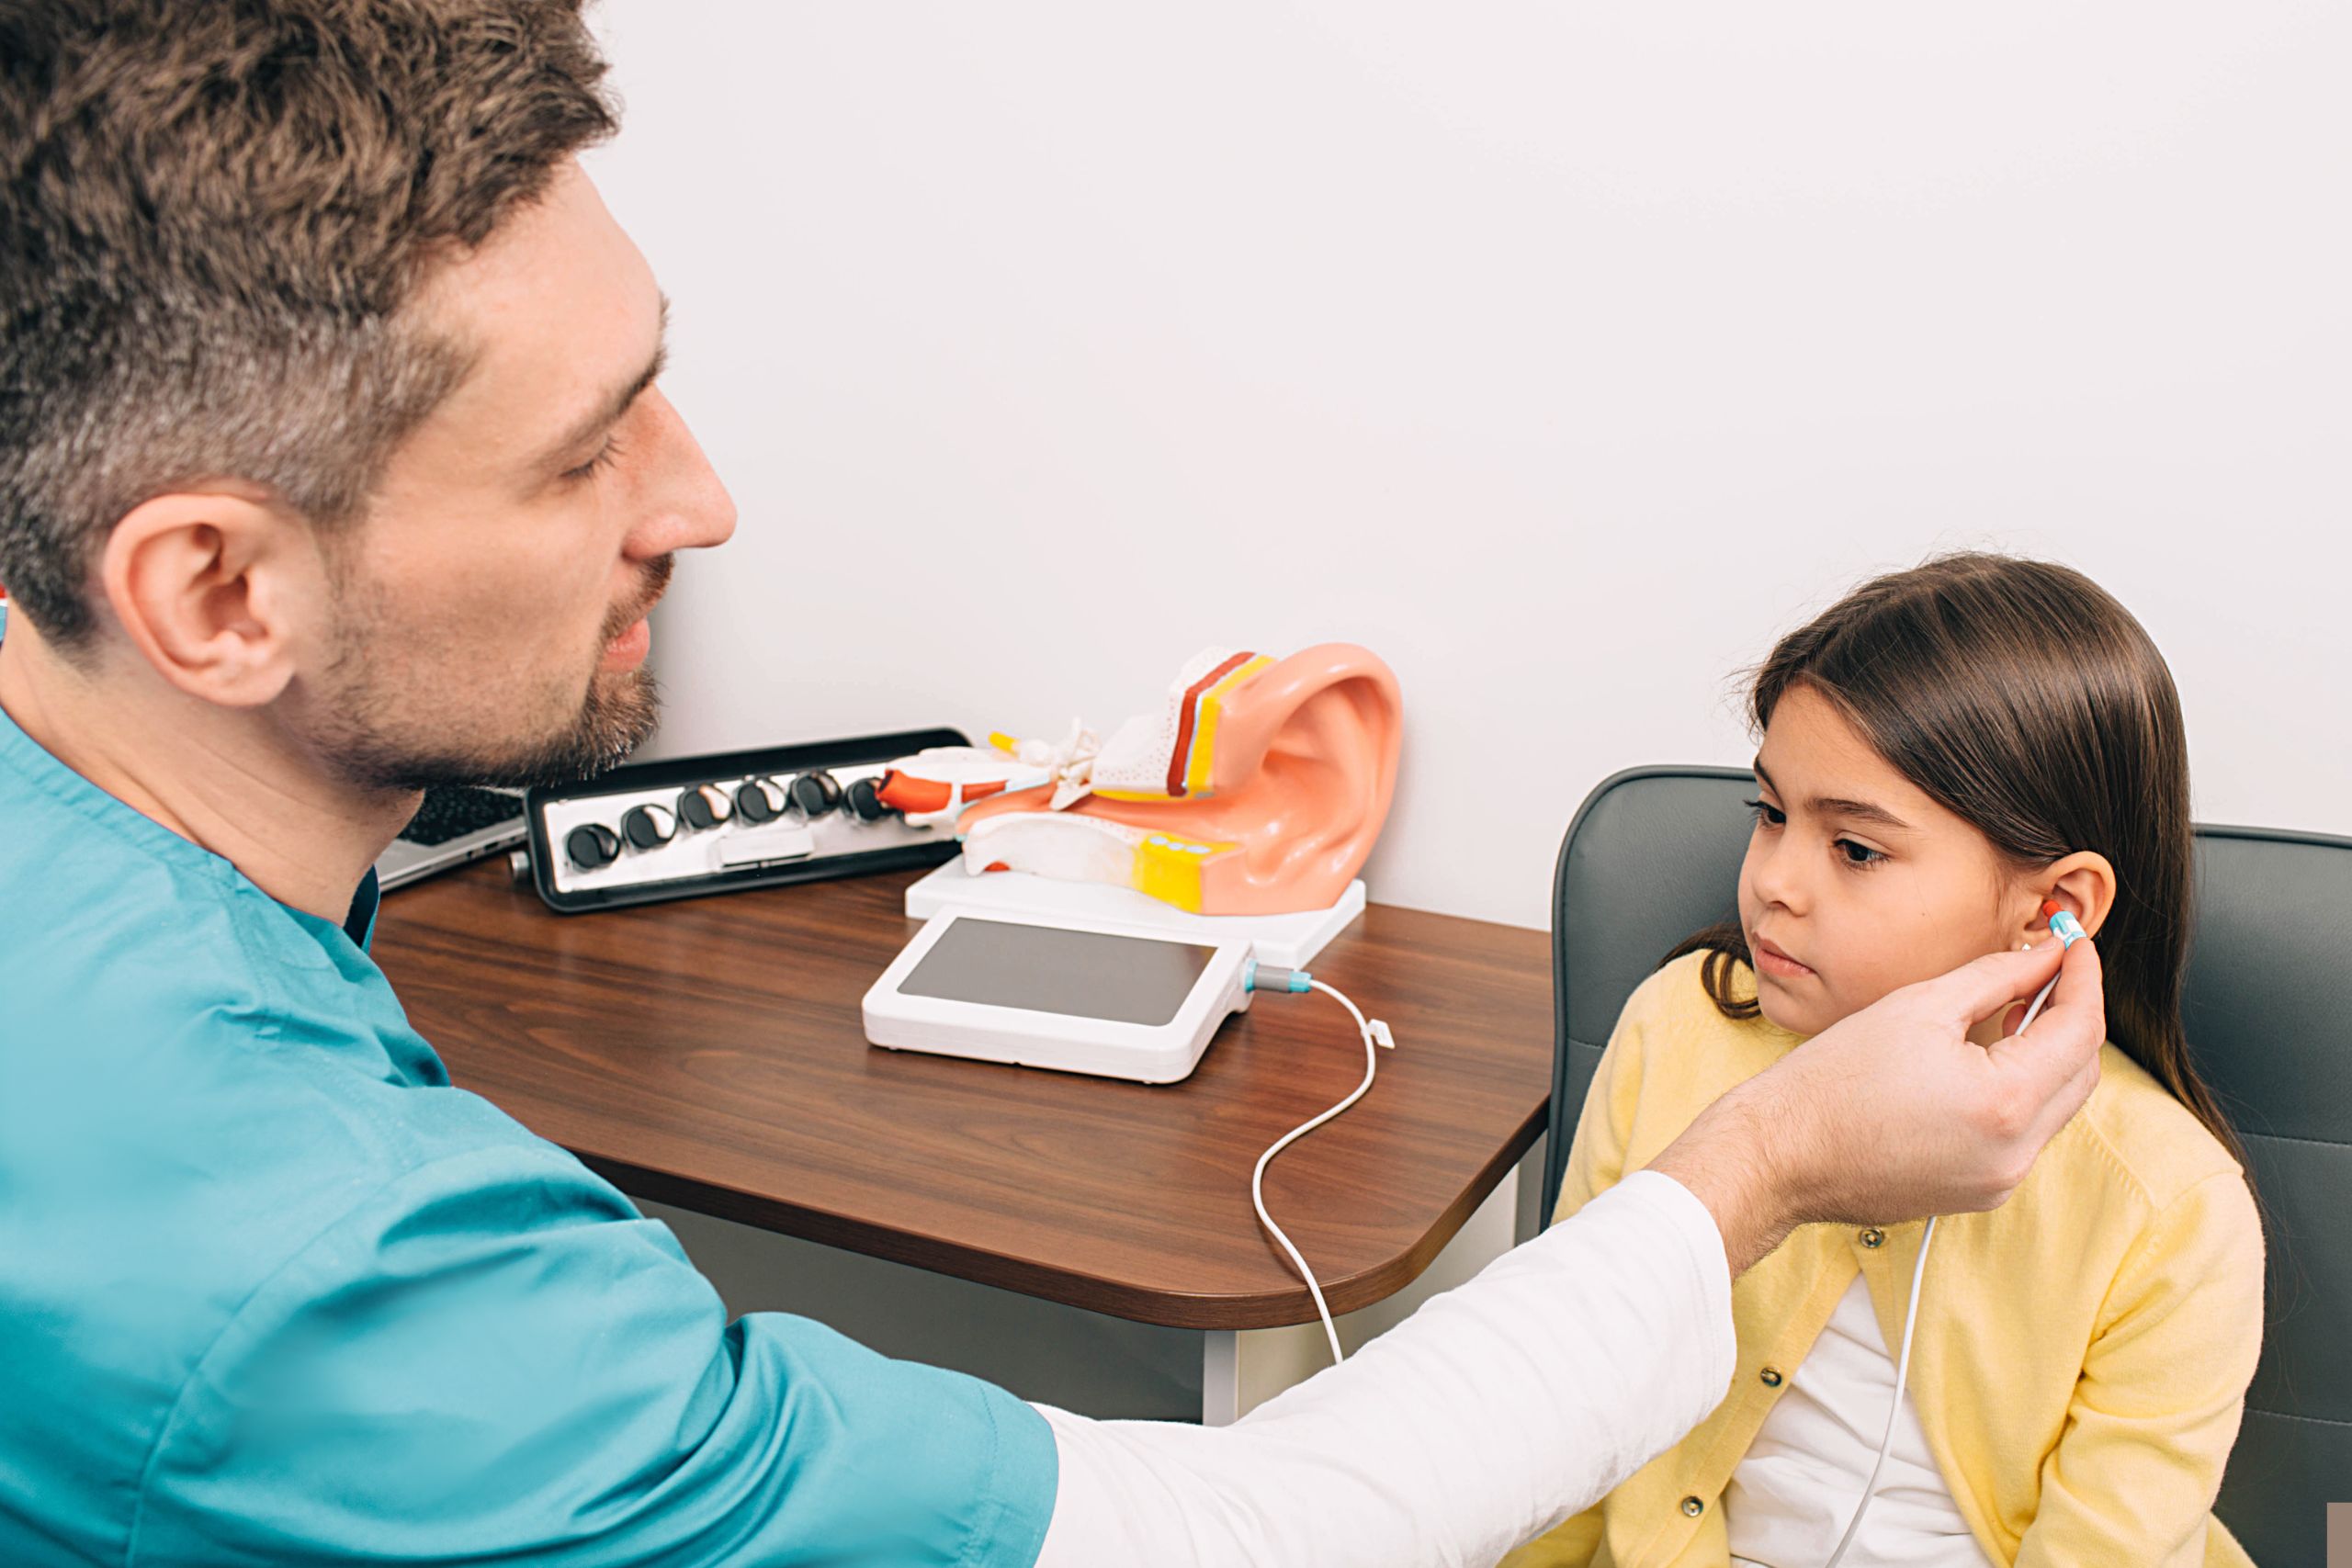
Ear infections are close to universal in early childhood. According to the National Institute on Deafness and Other Communication Disorders, five out of six children have at least one ear infection by their third birthday. Most of those children go on to maintain typical hearing function and develop speech normally. But sometimes, chronic ear infections can lead to a degree of hearing loss which requires the intervention of a Fort Myers speech therapist. Understanding which situations warrant attention requires understanding what fluid in the middle ear actually does to sound.
Sound Through Water
Fluid behind the eardrum does not usually produce deafness. It produces a mild conductive hearing loss, often in the range of 15 to 40 decibels, which functions something like listening with a finger in each ear. Speech remains audible. Detail does not.
The bigger issue is inconsistency. Fluid accumulates, clears, and returns. A child may hear clearly one week, poorly the next, and moderately well the week after. The brain is attempting to build a sound system out of input that keeps changing, during the exact window when it is doing the most learning.
Language development runs at peak intensity between roughly 12 months and four years. A child learning that words have consistent forms needs consistent evidence.
The Sounds That Disappear First
Mild hearing loss does not affect all speech equally. The elements that vanish are the quiet, high-frequency, and unstressed ones:

Rigidity and Routines: When Flexibility Becomes the Goal
Every household with young children runs on routine. Bedtime happens in an order. The same book gets read for months. Most families barely notice.
For some children, routine is not a preference. It is structural. The blue cup is not the preferred cup, it is the only cup. The route to school cannot change. A shirt with a tag in the wrong place ends the morning. Parents usually notice the shift from charming to consuming somewhere around the point where the family stops accepting dinner invitations. When things don’t happen as expected, you can expect a major meltdown.
But, as our Fort Myers ABA therapists can explain, that kind of rigidity can be a roadblock to independence for kids with autism.
Routines Are a Comfort for Kids With Autism
Insistence on sameness appears in the diagnostic criteria for autism as part of restricted and repetitive patterns of behavior. It is easy to read that as a symptom to be removed. That reading misses what the behavior accomplishes.
A substantial body of research points to intolerance of uncertainty as a mechanism underneath rigid routines. Research published in the Journal of Autism and Developmental Disorders has found that once intolerance of uncertainty is accounted for, autism diagnosis no longer significantly predicts anxiety levels. The difficulty is not with routine. The difficulty is with not knowing what happens next.
Seen that way, a rigid routine is a prediction a child can trust. Sameness lowers the number of unknowns the nervous system has to process at once. A child who insists the sequence never varies has found a strategy that works, which is why it is defended so fiercely.
That framing changes the clinical starting point. Behavior that serves a function does not respond well to removal. It responds to being replaced with something that serves the same function more efficiently.