
Blog

When Insurance Cuts Your Child’s Authorized Hours
When a letter arrives indicating your health insurance provider is cutting your child’s authorized therapy hours, it often lacks a clear explanation. Families receiving Fort Myers ABA therapy, speech therapy, and occupational therapy at FOCUS Therapy have more than once expressed frustration with the dense language in these letters, as well as the seemingly arbitrary cuts and no clear sense of what to do next.
When the number of hours your insurer is authorizing does not match the evidence-based recommendations of your child’s experienced, multidisciplinary therapy team, we will work families to help advocate for coverage of the services your child needs to reach their goals.
Note that the following is not a substitute for one-on-one advice and it may not cover your exact situation. Rather, it is a general map of the process so you know what questions to ask, what deadlines to watch, and who to call first.
What a Reduction in Therapy Hours Actually Means
Insurance authorization is the process by which a plan agrees in advance to pay for a set amount of service over a set period. When a plan reduces hours, it is saying the paperwork in front of its reviewer did not establish medical necessity for the amount requested.
That is a narrow finding, made usually in minutes by someone who has never watched your child work, often based on a few key words in a file. Reviewers see numbers and narrative summaries. They do not see the session where your daughter requested something with words for the first time, or the month your son stopped bolting in the parking lot.
Progress can even work against a request, because plans sometimes read improvement as evidence that less support is needed. But at FOCUS Therapy, our therapists understand that emerging are also the skills most likely to be lost without continued practice.

The Age of Toys Is Not Over: What Toy Story 5 Gets Right About Screens and Child Development
Pixar spent four films asking what happens to a toy when a child outgrows it. Toy Story 5 asks a harder question: What happens to a child when nothing gets outgrown, because nothing gets played with?
Bonnie is 8 now. She still plays with Jessie and Bullseye, but she cannot seem to make friends with the other kids in the neighborhood, because no one plays with toys anymore.
A discarded toy delivers the film’s thesis in five words: “The age of toys is over!”
Jessie climbs onto a roof and sees screens glowing in every house on the block. Bonnie’s parents buy her the frog-shaped tablet, Lilypad, with the hope that it help her socialize more with kids her own age.
Our Fort Myers ABA therapists recognize that the movie’s point is not that screens are all bad. It is that “toys are for play, but tech is for everything.” What Bonnie needed was another kid in the room. No device could be one. Screens do not harm children by doing something to them. The harm is in the hours of social-emotional development they are losing as a result. The impacts can be even more outsized for children with diagnoses like autism and ADHD who area already struggling with important life skills like interpersonal communication and impulse control.
What Kids Lose With Too Much Screen Time
The American Academy of Pediatrics focused not on the mechanism but the displacement in its February 2026 policy statement, Digital Ecosystems, Children, and Adolescents. High quality media built around children’s developmental needs can support learning and well-being. But media built to maximize engagement and commercialization encourages prolonged use — and that prolonged use displaces sleep, movement, and social development. The AAP states plainly that media and children “cannot be viewed solely through the lens of individual child behaviors or screen limits alone.”
The AAP’s current framework replaces the old clock-based rule with five questions, the 5 C’s: Child, Content, Calm, Crowding out, and Communication. Crowding out is the one that matters most here. What is the device getting in the way of?
For most children, the answer is sleep, movement, and other people – in that order.
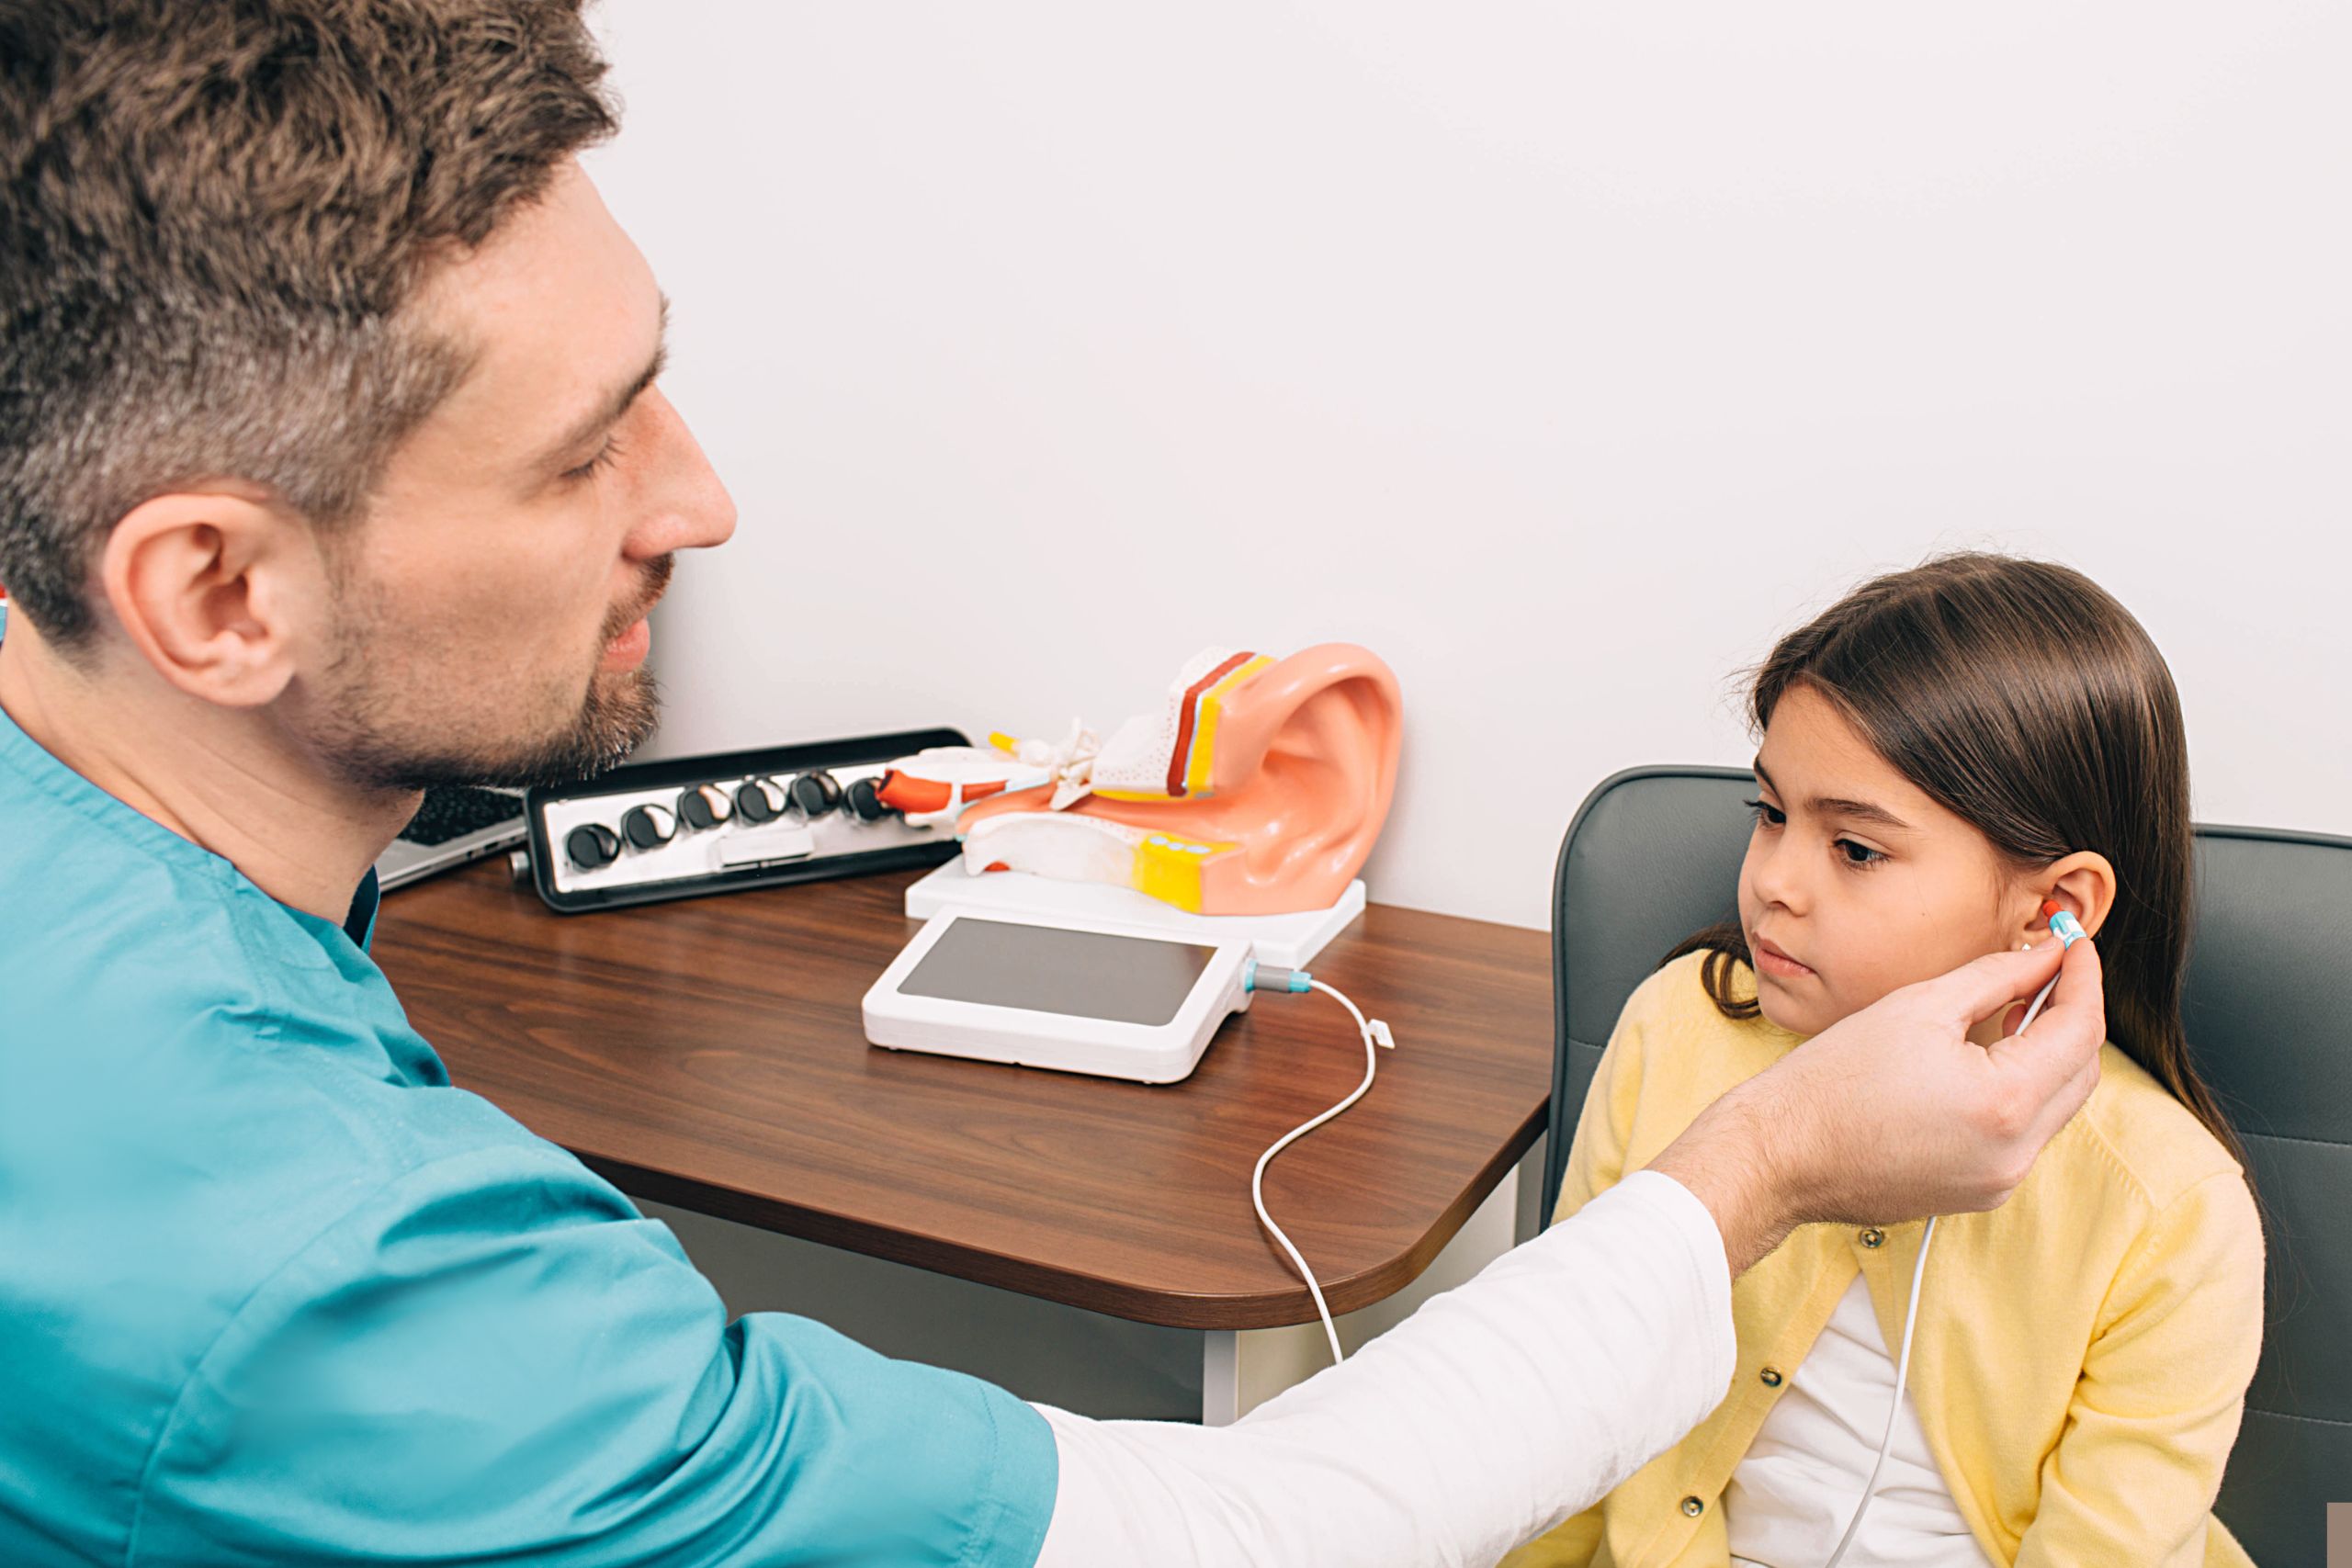
Hearing Loss, Chronic Ear Infections, and Delayed Speech
Ear infections are close to universal in early childhood. According to the National Institute on Deafness and Other Communication Disorders, five out of six children have at least one ear infection by their third birthday. Most of those children go on to maintain typical hearing function and develop speech normally. But sometimes, chronic ear infections can lead to a degree of hearing loss which requires the intervention of a Fort Myers speech therapist. Understanding which situations warrant attention requires understanding what fluid in the middle ear actually does to sound.
Sound Through Water
Fluid behind the eardrum does not usually produce deafness. It produces a mild conductive hearing loss, often in the range of 15 to 40 decibels, which functions something like listening with a finger in each ear. Speech remains audible. Detail does not.
The bigger issue is inconsistency. Fluid accumulates, clears, and returns. A child may hear clearly one week, poorly the next, and moderately well the week after. The brain is attempting to build a sound system out of input that keeps changing, during the exact window when it is doing the most learning.
Language development runs at peak intensity between roughly 12 months and four years. A child learning that words have consistent forms needs consistent evidence.
The Sounds That Disappear First
Mild hearing loss does not affect all speech equally. The elements that vanish are the quiet, high-frequency, and unstressed ones:

Rigidity and Routines: When Flexibility Becomes the Goal
Every household with young children runs on routine. Bedtime happens in an order. The same book gets read for months. Most families barely notice.
For some children, routine is not a preference. It is structural. The blue cup is not the preferred cup, it is the only cup. The route to school cannot change. A shirt with a tag in the wrong place ends the morning. Parents usually notice the shift from charming to consuming somewhere around the point where the family stops accepting dinner invitations. When things don’t happen as expected, you can expect a major meltdown.
But, as our Fort Myers ABA therapists can explain, that kind of rigidity can be a roadblock to independence for kids with autism.
Routines Are a Comfort for Kids With Autism
Insistence on sameness appears in the diagnostic criteria for autism as part of restricted and repetitive patterns of behavior. It is easy to read that as a symptom to be removed. That reading misses what the behavior accomplishes.
A substantial body of research points to intolerance of uncertainty as a mechanism underneath rigid routines. Research published in the Journal of Autism and Developmental Disorders has found that once intolerance of uncertainty is accounted for, autism diagnosis no longer significantly predicts anxiety levels. The difficulty is not with routine. The difficulty is with not knowing what happens next.
Seen that way, a rigid routine is a prediction a child can trust. Sameness lowers the number of unknowns the nervous system has to process at once. A child who insists the sequence never varies has found a strategy that works, which is why it is defended so fiercely.
That framing changes the clinical starting point. Behavior that serves a function does not respond well to removal. It responds to being replaced with something that serves the same function more efficiently.

How Autism In Girls Presents Differently
The mental image most people carry of autism is a boy. He lines up his cars, he does not make eye contact, he knows everything about trains. That picture is accurate for many children and incomplete for many others, and the children it fits least well are girls.
Autistic girls are identified later than boys, and some are not identified at all until adolescence or adulthood. The reason is not that autism is rare in girls. The reason is that the behaviors clinicians were trained to look for describe a presentation more common in boys.
What the Numbers Show and What They Conceal
The CDC’s Autism and Developmental Disabilities Monitoring Network identifies autism in about 1 in 31 eight-year-old children, and reports it as more than three times as common among boys as among girls. That ratio has been treated for decades as a fact about autism itself.
Research suggests it is partly a fact about diagnosis. A systematic review and meta-analysis published in the Journal of the American Academy of Child and Adolescent Psychiatry found that among children who actually meet criteria for autism, the true male-to-female ratio is closer to 3:1 than the commonly cited 4:1. The authors concluded that a diagnostic gender bias exists, and that girls who meet diagnostic criteria face a disproportionate risk of never receiving the diagnosis.
Later CDC surveillance supports the idea that identification is improving. Among 8-year-olds, the network reported 3.4 boys for every girl. Among 4-year-olds, that figure narrowed to 2.8. Younger cohorts are being screened with more awareness of what to look for.
The Differences Clinicians See
The distinctions below reflect patterns, not rules. Plenty of autistic girls present in ways traditionally associated with boys, and plenty of boys present in the ways described here.

- Restricted interests often look socially acceptable. Horses, dolls, a particular book series, or a celebrity draw less attention than an interest in ceiling fans, even when the intensity and rigidity are identical.
- Social motivation is frequently present. Many autistic girls want friendships very much, which leads observers to rule out autism based on desire rather than skill.
- Friendship patterns tend toward one intense attachment rather than isolation, and difficulty often surfaces when that friendship ends or the friend moves on.
- Social skills may be rehearsed rather than intuitive. A girl who has memorized scripts from television and from watching peers can appear socially fluent in short interactions and struggle badly in unstructured ones.
- Distress commonly appears at home rather than at school, arriving as an evening collapse after a day of holding it together.
- Difficulties present as anxiety, perfectionism, selective eating, or shutdown more often than as visible disruption.
Masking and Its Cost
Camouflaging describes the effort of suppressing autistic behaviors and imitating neurotypical ones. Girls tend to do it earlier, more consistently, and more successfully than boys.

Global Developmental Delay: What it Means and How FOCUS Therapy Can Help
Some diagnoses arrive with a folder of information. Global developmental delay usually arrives as a phrase at the end of a pediatric appointment, written on a referral form, sometimes with no explanation attached. Parents leave holding a term they have never heard, and the internet search that follows tends to make things worse instead of clearer.
At FOCUS Therapy, we want to ensure parents understand every aspect of their child’s condition because when you don’t understand something, you can’t address it. And when it comes to pediatric therapy, parents are our most critical partners in progress.
What the Term Actually Describes
Global developmental delay describes significant delay in two or more areas of development in a child under the age of five. “Significant” is not a matter of impression. Clinicians generally apply the standard of performance at least two standard deviations below the average for a child’s age on standardized, norm-referenced testing.
Developmental researchers group the areas of development into five domains:
- Gross and fine motor skills
- Speech and language
- Cognition
- Social and personal development
- Activities of daily living, such as feeding, dressing, and toileting
A delay confined to one domain gets a more specific name. A child behind only in speech has a speech or language delay, while a child behind in speech and also in motor skills and self-care falls under the broader description. Estimates place the prevalence at roughly one to three percent of children under five, which makes it one of the most frequently encountered developmental conditions in pediatrics.
Why Young Children Receive This Label Instead of Another
The single most useful thing a parent can understand about this diagnosis is that it is descriptive rather than explanatory. It states what a child’s development looks like right now. It says nothing at all about why.

When Speech Therapy Ends: Knowing Your Child Is Ready to Graduate
Here is a little secret about great speech therapy: from the very first session, our goal is to work ourselves out of a job. Every game, every silly sound, every “say it one more time” is quietly building toward a wonderful day when your child no longer needs us. At FOCUS Therapy, our approach to Fort Myers speech therapy is is never to hold them in place. That includes not keeping a child in therapy one minute longer than they truly need to be there.
So when speech therapy ends, it is not a door closing. It is a graduation. And like any graduation, it deserves celebration!
Graduation Is the Goal, Not the Goodbye
It is easy to treat therapy ending as something to worry about. We see it differently. A child graduating from speech therapy means the plan worked. The skills are theirs now, ready to carry into classrooms, playgrounds, dinner tables, and every conversation ahead. That is the whole point. We measure our success not by how long a child stays, but by how confidently they leave.
What “Ready” Looks Like
Graduation is never a guess. Speech-language pathologists look for clear, evidence-based signs before recommending that therapy wrap up. According to the American Speech-Language-Hearing Association’s guidance on discharge, the decision rests on a child’s individual and functional needs rather than a one-size-fits-all checklist.
A few signals tend to light up across the board. A child has met the goals their team set together. Their communication has caught up to what is expected for their age. And, importantly, the new skills have generalized, which is the therapy word for “show up everywhere,” not just in the quiet of the therapy room but at home, at school, and in the happy chaos of a busy birthday party.
What that looks like depends a lot on the child, because every road to graduation is a little different. For a child who came in working on tricky speech sounds, readiness might mean producing that once-stubborn “r” clearly in everyday conversation. For a little one building language, it might mean asking questions, telling stories, and keeping up with classmates. For a child working on fluency, it might mean carrying a toolkit of strategies and the confidence to use them. For a child building social communication, it might mean trading ideas and reading the room with friends. All different paths and often different destinations.
It Is Okay to Feel a Little Nervous
If the idea of ending therapy makes you a touch anxious, know that you aren’t alone. Many parents wonder whether the progress will hold, or whether their child is truly ready, or simply feel attached to a therapist who has become a trusted part of the week. All of that is normal. Just know that at FOCUS, we aren’t signing off until we’re sure it’s the right decision.
Graduation is a clinical decision built on real data, and skills that have genuinely generalized tend to stay put. Your child is not losing a safety net. They are showing the world they can soar without one.
The Support Does Not Stop at the Door
Graduating from regular sessions does not mean you are suddenly on your own. Good Fort Myers speech therapy comes with a plan for what is next.
Before discharge, your therapist will share doable strategies you can can continue to weave into ordinary moments at home. Many families also stay connected through periodic check-ins or a follow-up screening down the road, just to confirm everything is going well. (And we always love reconnecting with our former patients!) And if a future transition raises a fresh question, your child can always come back for a tune-up. Returning is not a step backward. It is simply smart, responsive care that grows along with your child.
Celebrating the Next Chapter
At FOCUS Therapy, we cheer the loudest on graduation day, because it means a child is stepping into their future with a stronger, more confident voice. That is exactly what every parent hopes for, and it is exactly what great Fort Myers speech therapy is built to deliver.
If your family is wondering where your child stands, whether you are just beginning the journey or starting to sense the finish line, we would love to talk. Reach out to the team at FOCUS to learn more about Fort Myers speech therapy, celebrate the milestones your child has already reached, and map out the bright road ahead. Visit focusflorida.com to schedule a visit today.
FOCUS Therapy offers Speech Therapy in Fort Myers, Florida. Call (239) 313.5049 or Contact Us online.
More Blog Entries:

School Services vs. Private Therapy: Why Your Child May Need Both
When we talk about speech therapy services at school versus in a private clinic like FOCUS Therapy in Fort Myers, the word “versus” makes it sound like a cage match. School services in one corner, private therapy in the other, and a parent stuck picking a winner. But the truth is: many children benefit from receiving both.
School-based and private speech therapy are not competitive. In fact, they are different operations with different aims and resources. For for a lot of kids, there is a significant benefit to having these two teams, especially if they can communicate or even collaborate.
If your family is trying to sort out the right balance for your child, it’s important to understand why having additional supports can be beneficial both in and out of the classroom.
Different Operations, Different Jobs
The biggest difference comes down to why each kind of therapy exists in the first place.
School-based speech services live under a federal law called the Individuals with Disabilities Education Act, or IDEA. Their job is educational. A school speech-language pathologist helps a child access and participate in their education, and eligibility depends on whether a communication issue adversely affects the child’s educational performance. Here is a nuance many parents miss: according to the American Speech-Language-Hearing Association, “educational performance” is not limited to report card grades. It includes how a child communicates, participates, and functions across the whole school day. These services come at no cost to families, which is wonderful.
Private speech therapy services like FOCUS are more centered on medical necessity. A clinic-based therapist asks whether a child has a communication need that affects their life and can be addressed, whether or not it is showing up in the classroom yet. Because young children are building skills for the first time, this work is often habilitative, meaning it helps a child develop abilities rather than recover lost ones. Private services are usually billed through insurance or paid privately.
Why a Child Can Qualify for One and Not the Other
This is the part that surprises, and sometimes frustrates, families. Because the two systems use different yardsticks, a child can clearly qualify for one and not the other.
Picture a bright kindergartner with a mild articulation difference. Their grades are fine, they are keeping up in class, and the school determines that the issue does not adversely affect educational performance. That is a completely valid call under IDEA. That same child, evaluated at a clinic, may well qualify for private therapy, because the difference is real, it affects how easily they are understood, and it can be treated now rather than later.
So if you ever receive a letter saying your child does not qualify for school services, take a breath. It is not a verdict on whether your child needs help. It is one system applying one specific standard. A private evaluation may tell a different story.
It Is Often Not Either / Or
Even when a child qualifies for both, the two settings tend to look quite different, and that is by design.
School speech therapy often happens in small groups or right inside the classroom, because the law encourages keeping kids in their least restrictive environment alongside their peers. Caseloads are large and minutes are precious, so sessions may be brief and shared.
Meanwhile, private speech therapy in Fort Myers is most often one on one. It can be more frequent, more intensive, and tailored right down to the individual goal. It also offers flexibility that school cannot, including after-school appointments, parent coaching, and the thing every parent of a busy learner appreciates most, continuity through summer break.
The scope can differ too. A private therapist has room to address communication wherever it lives, from making friends on the playground to feeding challenges at the dinner table, even when those goals reach beyond the school day.
The Power of a Team
When school and private therapy are provided in tandem, your child gets something powerful: practice in more places, with more people, toward the same goals. Skills learned in a quiet therapy room need to travel to the classroom, the kitchen, and the carpool line. The more settings a child practices in, the more those skills stick, a concept therapists call generalization.
Two teams pulling in the same direction also means fewer gaps.
Private speech therapy can keep momentum going over the summer and school holidays, so September does not begin with a frustrating backslide. And when everyone is communicating, your child gets one consistent, encouraging message instead of two disconnected ones.
Where FOCUS Fort Myers Speech Therapists Come In
This is exactly the role private therapy is built to play. At FOCUS, a multidisciplinary pediatric clinic, our Fort Myers speech therapists provide the individualized, one-on-one support that complements whatever your child receives at school. They can dig into goals the school day does not have time for, coach you on simple strategies to use at home, and, with your permission, collaborate with the school team so everyone is rowing in the same direction.
The best Fort Myers speech therapists are not trying to replace your child’s school. We’re trying to surround your child with support, so progress can happen everywhere your child happens to be.
You do not have to choose between school and private therapy, and you do not have to figure it out alone. The team at FOCUS would love to evaluate your child, explain your options in plain language, and help you build a plan that fits your family. Reach out to connect with the Fort Myers speech therapists at FOCUS, and let’s give your child every chance to find their voice. Visit focusflorida.com to schedule a visit today!
FOCUS Therapy offers Speech Therapy in Fort Myers, Florida. Call (239) 313.5049 or Contact Us online.
More Blog Entries:

Potty Training a Child With Developmental Delays
Few parenting milestones come with as much pressure, mythology, and unsolicited advice as potty training. Everyone has a cousin whose toddler trained in a weekend, a neighbor with a foolproof sticker chart, and a strong opinion about how soon is too soon. When your child has a developmental delay, all of that noise can feel especially loud. So here is the good news is that while your road may have a few more pit stops than others, but the destination is the same. Our Fort Myers occupational therapists and ABA therapists at FOCUS Therapy are here to help.
Take a deep breath, lower the stakes, and let’s talk about how to make this milestone less of a standoff and more of a team effort.
Forget the Calendar, Watch the Child
The single most freeing idea in potty training is this: readiness is about skills, not birthdays. The American Academy of Pediatrics points out that there is no single right age to start, and that children typically show signs of bladder and bowel control somewhere between 18 and 24 months. For a child with developmental delays, those signs often arrive later, and that is completely normal. The AAP itself notes that kids with special health care needs may need the usual tips adjusted.
So what are you actually watching for? A few friendly clues that the body and brain are getting in sync. Your child stays dry for a couple of hours at a stretch. They notice the moment something is happening, maybe with a pause, a grunt, or a telltale squat behind the couch. They can follow a simple instruction, and they can manage the engineering challenge of pulling pants up and down. None of this has to be perfect. These are the green lights, not a final exam.
Readiness Can Look a Little Different, and That Is Okay
Here is where the standard advice needs a gentle remix. Some children with developmental delays or autism are slow to show the classic readiness signs, and a few may not show them in the textbook way at all. Research suggests that around half of four- and five-year-olds on the autism spectrum are not yet fully toilet trained, compared to a much smaller share of their peers. That number is not a warning. It is permission to stop comparing and start meeting your child where they are.
The trick is balance. You do not want to rush a child who is not ready, but you also do not want to wait forever for a sign that may be quiet or unusual. If most of the building blocks are there, it is okay to begin, even if your child is a little older than the books suggest.
Small Steps, Big Wins
Potty training is not one skill. It is a whole stack of them wearing a trench coat. There is noticing the urge, getting to the bathroom, managing clothing, sitting, relaxing the right muscles, wiping, flushing, and washing up. For any child that is a lot. For a child who learns best in small, concrete pieces, it helps to teach each part on its own and stitch them together over time.
This is where structure really shines. Predictable bathroom times, simple visual schedules that show the steps in order, and plenty of cheerful reinforcement when things go right all give a child something steady to lean on. Picture-based routines are not just cute. They turn an abstract process into a clear sequence your child can follow, and they let the schedule be the boss so you do not have to play nag.
A quick word about accidents, because there will be accidents. They are not setbacks. They are data. Each one tells you a little more about timing, cues, and what your child needs next. Keep it light, keep it kind, and keep the bathroom a no-shame zone.
The Sensory Side of the Stall
Sometimes the holdup is not motivation at all. It is the experience itself. A toilet can be a strange and slightly alarming place for a sensory-sensitive kid. The seat is cold and oddly shaped. The flush is loud and sudden. The room echoes, the floor feels far away, and the whole event happens over a mysterious hole of swirling water. If your child resists the bathroom itself, the issue may be sensory rather than stubborn.
Small adjustments can work wonders here.
A sturdy step stool gives little feet a place to push and makes the throne feel less like a cliff. A cushioned seat reducer shrinks the target. Flushing after your child has stepped away can take the startle out of the moment. These are not gimmicks. They are the kind of practical, child-centered tweaks that turn a scary stall into a manageable one.
Where a Fort Myers Occupational Therapist Comes In
Here is a fact that surprises a lot of families: toileting is officially an occupational therapy skill. In the therapy world, the everyday tasks of being a person, including dressing, eating, and yes, using the bathroom, are called activities of daily living, and helping kids master them is a core part of what occupational therapists do.
A pediatric occupational therapist looks at the whole puzzle. They can sort out whether a sticking point is really a motor issue, like trouble with buttons and waistbands, a sensory one, like an aversion to the sound or the seat, or a sequencing one, like losing the thread of the steps. Then they build a plan around your specific child, often turning practice into play so the pressure melts away. At FOCUS, a multidisciplinary clinic, a Fort Myers occupational therapist works alongside speech and physical therapists, so if a delay touches more than one area, the whole team is already in the room.
The best part is the relief. Many families arrive feeling stuck and leave with a clear, doable plan and a lot less worry.
Ready to Make Peace With the Potty?
If potty training has turned into a daily power struggle, you do not have to keep guessing. The team at FOCUS would love to help you trade the frustration for a friendly, step-by-step plan that fits your child. Reach out to schedule a visit with a Fort Myers occupational therapist, and let’s get your little one flushing with pride. Visit focusflorida.com to book an appointment today.
FOCUS Therapy offers Occupational Therapy and ABA Therapy in Fort Myers, Florida. Call (239) 313.5049 or Contact Us online.
More Blog Entries:

Late to Walk? Gross Motor Milestones and When to Take the Next Step
There is a special kind of suspense that comes with waiting for a baby’s first steps. The phone camera is charged, the grandparents are on standby, and every wobble near the coffee table feels like the big moment. Then a friend’s baby starts walking at ten months, yours is happily scooting around at fourteen, and that suspense quietly turns into worry. Take a breath. In most cases, a later walker is simply a baby moving on their own perfectly typical development schedule. That said, you should also trust your gut. If you do have concerns, we encourage you to reach out to FOCUS to consult with a Fort Myers occupational therapist for an objective professional opinion.
What “On Time” Really Looks Like
The truth is that the window for walking is wide. According to the World Health Organization’s motor development study, healthy children take their first independent steps anywhere from about 8 months to nearly 18 months, with the average landing right around the first birthday. That is close to a full year of “normal.” A baby who walks at nine months and a baby who walks at sixteen months can both be developing beautifully.
The CDC’s milestone checklist lists walking without holding on as something most children do by 18 months. The important phrase there is “most children.” These checklists are set at the age by which about three out of four kids have a skill, which makes them a gentle nudge to check in rather than a hard deadline.
The Road to Those First Steps
Walking does not happen overnight. It is the grand finale of a whole series of gross motor milestones. Babies usually roll over, then sit without support, then pull up to stand, and then cruise along the furniture like a tiny commuter gripping the railings. Each stage builds the strength, balance, and confidence for the next one.
One happy surprise for many parents is that crawling is optional. In 2022 the CDC actually removed crawling from its milestone checklists, because plenty of healthy babies scoot, roll, or shuffle on their bottoms and skip the classic hands-and-knees phase entirely. If your little one never crawled and went straight to cruising, that is perfectly fine.
So when is “late” worth a closer look? A few signs are worth a friendly conversation with your pediatrician or a therapist. It makes sense to reach out if your child is not walking at all by 18 months, is not bearing weight on their legs or pulling to stand by around the first birthday, strongly favors one side of the body, or seems unusually stiff or floppy. Losing a skill they once had is always worth a same-week call.
None of these signs means something is automatically wrong. They simply mean it is a good time to take a closer look, and looking early is a gift. The earlier a child gets a little support, the more their growing, flexible brain can do with it.
How a Fort Myers Occupational Therapist Can Help
This is where a friendly team makes all the difference. At FOCUS, our multidisciplinary pediatric therapy clinic of speech therapists, occupational therapists, and ABA therapists work side by side to look at the whole child. A pediatric occupational therapist pays special attention to how motor skills power the everyday business of being a kid, from climbing at the playground to standing steady enough to stack blocks and self-feed.
If an evaluation turns out to be a good idea, just know that it’s not going to look like a stressful medical exam. With a skilled Fort Myers occupational therapist, it looks like play. Therapists turn balance, strength, and coordination work into games, so your child is having fun while building exactly the skills they need. And if everything checks out, you walk away with the best prize of all, which is peace of mind.
Ready to Trade Worry for Answers?
Reach out to schedule a consultation or evaluation with one of our Fort Myers occupational therapists. We’re here to celebrate every step along the way – no matter when it comes.
FOCUS Therapy offers occupational therapy in Fort Myers, Florida. Call (239) 313.5049 or Contact Us online.
More Blog Entries: